Overview
Bile duct cancer, or cholangiocarcinoma, is a rare cancer that starts in the bile ducts, the tubes that carry bile from the liver and gallbladder to the small intestine. Bile helps digest fats. The cancer can develop in ducts inside the liver (intrahepatic), at the point where the main ducts leave the liver (perihilar), or in the ducts outside the liver (distal).
Cholangiocarcinoma often causes no symptoms in its early stages, and when symptoms appear, such as yellowing of the skin and eyes (jaundice), itching, dark urine, pale stools, abdominal pain and weight loss, the cancer has often spread. It is more common in people over 65 and in parts of Southeast Asia, where liver fluke infections are common. Surgery offers the best chance of cure, and newer treatments, including targeted therapy and immunotherapy, have improved outcomes for advanced cancer.
When to get urgent help
Seek urgent care for yellowing of the skin and eyes, fever with chills, severe abdominal pain or confusion.
Causes and risk factors
- Primary sclerosing cholangitis (PSC), often with ulcerative colitis
- Liver fluke infections (Opisthorchis viverrini, Clonorchis sinensis) from raw freshwater fish, mainly in Southeast Asia
- Bile duct cysts (choledochal cysts)
- Bile duct stones and chronic inflammation
- Cirrhosis, hepatitis B and C
- Obesity, diabetes and fatty liver disease
- Alcohol and smoking
- Older age
- Exposure to some chemicals, such as thorotrast (historical) and possibly asbestos
How it develops (pathophysiology)
Normal bile ducts
Bile is made by liver cells and drains through tiny channels that join into larger bile ducts, forming the right and left hepatic ducts, which merge into the common hepatic duct. This joins the duct from the gallbladder to form the common bile duct, which passes through the pancreas to the duodenum. The ducts are lined by cholangiocytes, specialised cells that modify bile.
What goes wrong
- Chronic inflammation and injury: conditions such as PSC, liver fluke infections, stones and cysts cause long-term inflammation of the bile ducts.
- Cell damage and repair: inflammation releases cytokines (such as interleukin-6) and reactive oxygen species, which damage DNA in cholangiocytes and stimulate repeated cell division.
- Genetic changes: cholangiocytes accumulate mutations. Common changes include: - IDH1 and IDH2 mutations (intrahepatic) - FGFR2 fusions (intrahepatic) - KRAS, TP53, BAP1, ARID1A and HER2 changes
- Cancer growth: abnormal cells grow along the duct walls, often infiltrating surrounding tissue and nerves, and narrowing or blocking the ducts.
- Spread: cancer spreads to nearby lymph nodes, liver, blood vessels and the lining of the abdomen.
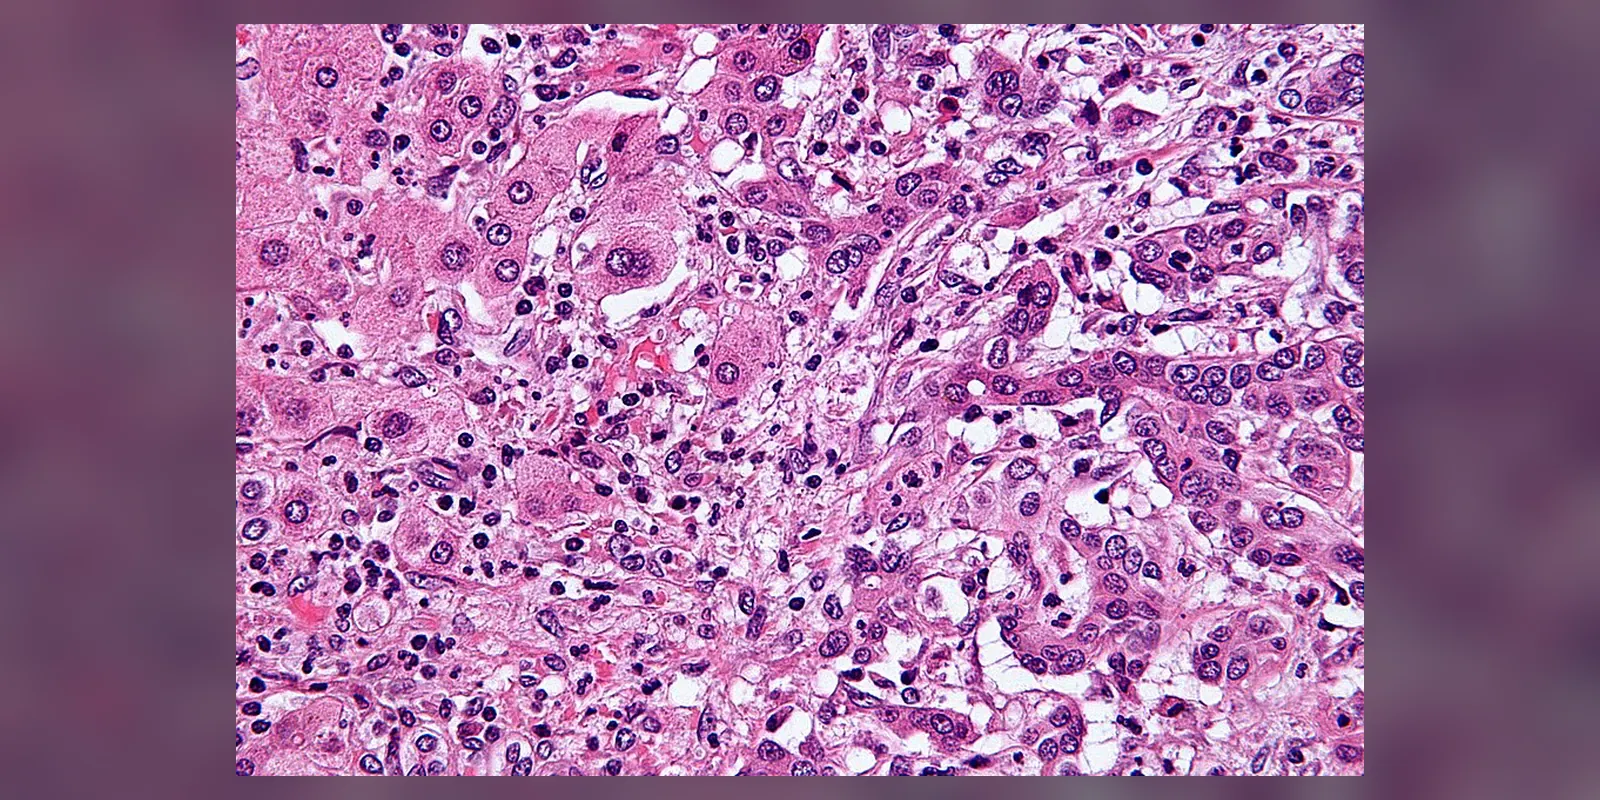
The tumour is often surrounded by dense scar tissue (desmoplastic stroma), which makes it hard to detect on scans and to treat.
Why the symptoms happen
- Jaundice: the tumour blocks bile flow, so bilirubin builds up in the blood.
- Itching: bile salts accumulate in the skin.
- Dark urine and pale stools: bilirubin is excreted in urine instead of reaching the bowel.
- Abdominal pain: tumour growth and liver stretching.
- Weight loss, tiredness and loss of appetite: effects of cancer and poor fat digestion.
- Fever: infection of blocked bile ducts (cholangitis).
How treatment acts on the mechanism
Surgery removes the tumour and affected bile ducts and liver. Stents placed by ERCP or through the skin relieve blockage, improving jaundice and itching. Chemotherapy (gemcitabine and cisplatin) combined with immunotherapy (durvalumab or pembrolizumab) slows cancer growth. Targeted therapies block specific mutations, such as FGFR inhibitors (pemigatinib, futibatinib) and IDH1 inhibitors (ivosidenib). Liver transplantation is an option for selected early perihilar cancers.
Types
- Intrahepatic cholangiocarcinoma: inside the liver
- Perihilar (Klatskin) cholangiocarcinoma: where the ducts leave the liver; the most common
- Distal cholangiocarcinoma: in the lower common bile duct
- Gallbladder cancer is a related but separate cancer
Signs and symptoms
- Yellowing of the skin and eyes
- Itchy skin
- Dark urine
- Pale, greasy stools
- Abdominal pain, often in the upper right side
- Unintentional weight loss
- Loss of appetite
- Tiredness
- Fever and chills (if the ducts become infected)
- Early stages may have no symptoms
How it is diagnosed
- Blood tests: liver function tests, tumour markers (CA19-9, CEA)
- Ultrasound
- CT scan and MRI with MRCP to assess the tumour and bile ducts
- ERCP with brushings or biopsy
- Endoscopic ultrasound with biopsy
- Liver biopsy for intrahepatic tumours
- PET-CT to check for spread
- Molecular testing of tumour tissue to guide targeted treatment
Possible complications
- Bile duct blockage
- Cholangitis
- Liver failure
- Malnutrition
- Spread to other organs
Goals of treatment
Treatment aims to remove the cancer where possible, relieve symptoms such as jaundice, extend life and maintain quality of life.
Medicines
- Chemotherapy: gemcitabine and cisplatin, often with durvalumab or pembrolizumab
- Adjuvant capecitabine after surgery
- Targeted therapies: FGFR2 inhibitors, IDH1 inhibitors, HER2-targeted therapies
- Second-line chemotherapy (such as FOLFOX)
- Medicines for itching, such as colestyramine
- Antibiotics for cholangitis
Other treatments
- Surgery: resection of the bile duct and part of the liver
- Liver transplantation in selected cases
- Biliary stenting via ERCP or percutaneous drainage
- Radiotherapy or local treatments (radiofrequency ablation, selective internal radiation therapy)
- Palliative care
Living with it and prevention
- Avoid eating raw or undercooked freshwater fish in areas with liver flukes
- Get vaccinated against hepatitis B
- Limit alcohol and stop smoking
- Maintain a healthy weight
- People with PSC should have regular monitoring
Monitoring and follow-up
After treatment, regular scans and blood tests check for recurrence. People with PSC are monitored for early signs of cholangiocarcinoma.
Outlook
The outlook depends on the stage and whether the cancer can be removed. Surgery offers the best chance of long-term survival. Advanced cancer has a poorer outlook, but newer treatments are improving survival.
Special considerations
- People with PSC: lifetime risk of cholangiocarcinoma is significantly higher
- People from Southeast Asia: liver fluke-associated cancer is more common
- Older adults: treatment is tailored to fitness